Introduction: Why Botox Aftercare Is Being Reconsidered
Botox aftercare is one of the most repeated areas of advice in aesthetic medicine. Patients are often told not to lie down, not to exercise, not to touch the treated area, to avoid heat and sun, and to remain upright for several hours after upper-face botulinum toxin injections. These instructions are familiar, but familiarity is not the same as strong evidence.
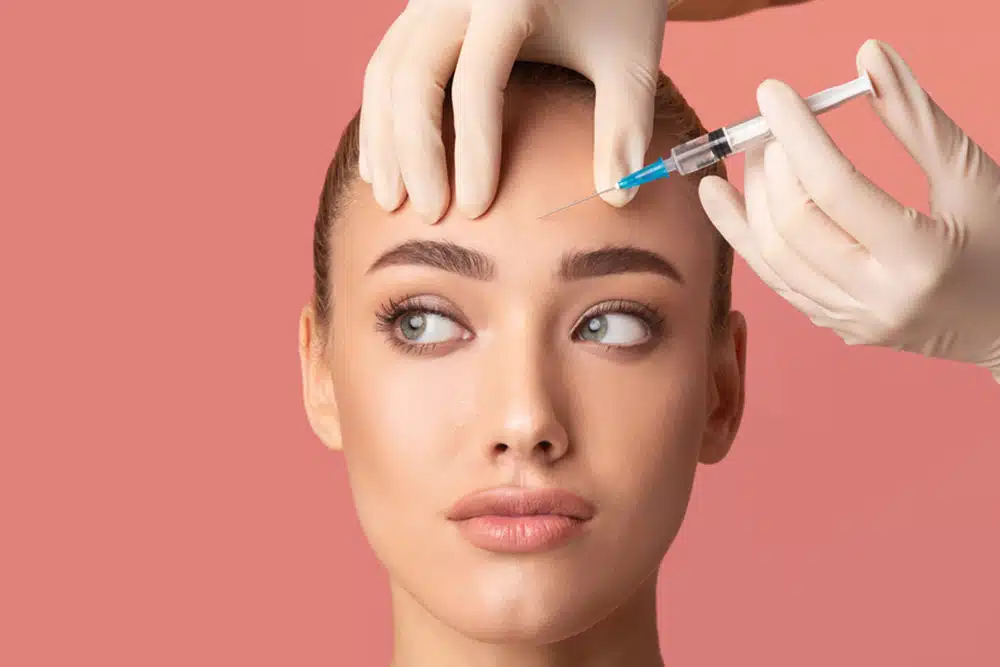
A 2025 paper published in Toxins asked a direct question: are extended post-care recommendations following upper-face botulinum toxin treatment scientifically necessary? The authors reviewed outcomes in more than 5,000 patients who received only a brief 10-minute immediate precaution period before returning to normal activities.
For patients searching for Botox in Abu Dhabi, this is an important discussion because aftercare should ideally be proportionate to the evidence, the treatment area, the product used, the dose, the patient’s anatomy and the clinician’s judgment—not simply a list of rules repeated because they have always been repeated.
What Traditional Botox Aftercare Usually Includes
The study lists several commonly recommended restrictions for the first hours after treatment:
- Avoiding facial expressions.
- Staying upright.
- Refraining from physical activity.
- Avoiding direct sun exposure.
- Avoiding heat sources.
The authors state that these recommendations are largely supported by anecdotal or theoretical reasoning rather than robust clinical trials specifically demonstrating that the restrictions reduce complications or improve durability.
How Botulinum Toxin Works—and Why Timing Matters
Botulinum toxin type A is a neuromodulator. At the neuromuscular junction it interferes with neurotransmitter release, including through cleavage of SNAP-25, reducing acetylcholine-mediated muscle contraction. In aesthetic practice, this is used to soften dynamic lines such as forehead lines, glabellar frown lines and lateral periorbital lines.
A central argument in the paper is that botulinum toxin binding and internalization occur relatively quickly. The authors therefore question whether behavioral restrictions extending for several hours continue to provide meaningful additional protection once the toxin has begun to act locally.
Important distinction: The study discusses local, dose-dependent diffusion rather than uncontrolled ‘migration.’ It also emphasizes that injection technique, dose selection and anatomical knowledge remain important when trying to minimize unwanted functional effects.
Who Was Included—and Who Was Not Treated
The source paper reports the following inclusion criteria:
- Age between 18 and 69 years.
- Dynamic or static wrinkles in the upper third of the face.
- A desire for facial rejuvenation.
The authors report that patients were not treated if they had:
- Contraindications to botulinum toxin type A listed by the authors, including keloidal scarring, body dysmorphic disorder, pregnancy and breastfeeding.
- Previous adverse reactions to botulinum toxin type A.
- Underlying neurological disorders that could interfere with treatment outcomes.
All patients signed informed consent outlining the purpose, expected outcomes, risks and benefits of treatment.
The Simplified Post-Treatment Protocol
Patients were observed in the clinic for 10 minutes after injection so that immediate adverse reactions could be identified. After that period, the study reports that no specific post-treatment instructions or restrictions were given, and patients were free to resume normal activities.
Patients were subsequently asked to return for clinical review and complete a satisfaction questionnaire. The paper contains a timing inconsistency: several sections describe follow-up at two weeks, while the satisfaction subsection states that satisfaction was assessed one month after treatment. This should be acknowledged rather than silently reconciled.
Results: What Adverse Effects Were Reported?
Of the 5,014 treated patients, 4,000 attended the scheduled clinical evaluation. The paper reports an overall adverse-effect incidence of approximately 6%, with no severe adverse reactions.
| Adverse effect | Number | Incidence |
| Mild bruising at injection site | 120 | 3.00% |
| Temporary headache | 72 | 1.80% |
| Eyebrow ptosis | 16 | 0.40% |
| Dry eyes | 12 | 0.30% |
| Other effects (e.g., muscle weakness, flu-like symptoms) | 20 | 0.50% |
| Upper-eyelid ptosis | 0 | 0% among evaluated follow-up patients |
The absence of observed upper-eyelid ptosis in the evaluated follow-up cohort is the study’s most attention-grabbing finding. However, a zero-event observation in a retrospective cohort should not be interpreted as proof that eyelid ptosis cannot occur after botulinum toxin treatment.
Patient Satisfaction
A total of 2,010 satisfaction questionnaires were collected. The table in the paper reports the following distribution:
| Satisfaction level | Patients | Percentage |
| Very satisfied | 1,005 | 50% |
| Satisfied | 804 | 40% |
| Neutral | 120 | 6% |
| Dissatisfied | 60 | 3% |
| Very dissatisfied | 21 | 1% |
Taken together, 90% of respondents were satisfied or very satisfied. One detail worth noting for editorial accuracy is that the narrative later in the paper appears to reverse the labels for the 3% and 1% dissatisfied categories, whereas the study’s Table 2 lists 3% as dissatisfied and 1% as very dissatisfied. The website article should therefore use the table values shown above.
. Myth vs Evidence: What Does the Study Actually Support?
| Common belief | What the source study supports | What it does NOT prove |
| ‘You must stay upright for 4 hours.’ | Patients in this cohort resumed normal activity after a 10-minute observation period without an observed upper-eyelid ptosis signal. | It did not randomize upright vs lying-down groups. |
| ‘Exercise will make Botox move.’ | Extended activity restriction was not part of the protocol. | It was not a dedicated strenuous-exercise trial. |
| ‘Facial movement must be avoided.’ | The authors say traditional restrictions lack robust evidence; they also discuss preliminary evidence that muscle activity may influence outcomes. | Long-term aesthetic superiority of movement vs no movement was not tested. |
| ‘Botox spreads freely around the face.’ | The discussion emphasizes local, dose-dependent diffusion. | It does not mean unwanted effects are impossible; technique and dose remain important. |
| ‘Ice is always beneficial after Botox.’ | The paper says cooling is common and discusses preliminary evidence that cooling may influence toxin translocation. | The study did not randomize icing vs no icing. |
| ‘All aftercare is unnecessary.’ | The paper challenges prolonged behavioral restrictions. | It does not eliminate the need for sterile technique, individualized advice, bruising precautions or clinical follow-up. |
Do I Really Need to Stay Upright After Botox?
The traditional four-hour upright rule is one of the best-known Botox instructions. In this study, however, patients were not kept under prolonged positioning restrictions after the initial 10-minute observation period, and no upper-eyelid ptosis was observed among those who returned for clinical follow-up.
The most accurate interpretation is therefore not ‘lying down has been proven safe in every situation,’ but rather that the scientific basis for a universal prolonged upright rule is weaker than many patients assume.
Can I Exercise After Botox?
Patients were free to resume normal activities after leaving the clinic. This makes the study relevant to the common recommendation to avoid exercise for several hours. However, the investigators did not specifically compare high-intensity exercise with rest, measure workout intensity, or randomize patients according to activity level.
The study questions the need for routine prolonged activity restriction after upper-face botulinum toxin, but it does not definitively prove that every form of strenuous exercise immediately after treatment has identical outcomes.
Can I Lie Down or Sleep After Botox?
The study challenges extended post-treatment positioning rules but did not create separate groups for lying down, sleeping and remaining upright. Therefore, it supports reconsidering rigid universal rules, while individualized clinical instructions remain reasonable when there is a specific concern.
Can I Touch or Massage My Face After Botox?
The paper discusses the common ‘no touch or massage’ rule in the context of toxin migration and local diffusion. Its discussion states that botulinum toxin acts locally and that diffusion is dose-dependent. Nevertheless, the study did not directly randomize massage versus no massage, so a claim that facial massage is proven harmless would go beyond the evidence.
Should I Avoid Heat, Sun or Sauna After Botox?
Avoiding direct sun and heat is listed among traditional recommendations. The study’s simplified protocol did not maintain extended restrictions, but the paper does not isolate heat exposure as a separate variable. It therefore challenges the universality of the rule without providing a dedicated heat or sauna trial.
What About Ice or Cooling?
Cooling the injection site is often used to reduce bruising or swelling. The authors note emerging research suggesting that cooling may potentially influence botulinum toxin translocation and could theoretically affect efficacy or
Does Botox ‘Migrate’?
The paper argues that ‘diffusion’ is a more accurate term than uncontrolled ‘spread.’ At recommended doses, botulinum toxin acts locally, and the extent of diffusion is influenced by dose. The discussion also emphasizes that serious complications such as ptosis can occur when injection placement, anatomy or technique are not appropriately managed.
Technique May Matter More Than Ritualistic Aftercare
One of the clinically important themes of the paper is that treatment safety is not simply determined by what a patient does for four hours after injection. The authors repeatedly point toward dose, placement, local action, injector expertise and anatomical knowledge as central considerations.
For a patient considering upper-face Botox in Abu Dhabi, this shifts the conversation from ‘How many hours must I sit upright?’ toward more meaningful questions: Was the treatment appropriately planned? Was the anatomy assessed? Was the dose individualized? Was the injection placement suitable for the patient’s muscle pattern?
Bruising and Injection-Site Care Still Matter
The paper does not argue that every precaution is unnecessary. Injection-site erythema, edema and ecchymosis are described as common minor effects. The authors emphasize sterile technique, makeup removal before treatment and attention to agents that can impair clotting as practical considerations for reducing bruising and infection risk.
Medication safety: The source discusses avoiding NSAIDs and agents that impair clotting as bruising precautions. Patients should not stop prescribed anticoagulants, antiplatelet therapy or other medically necessary medication without the advice of the clinician who manages that treatment.
Eyelid Ptosis vs Eyebrow Ptosis: Not the Same Thing
The study specifically highlights upper-eyelid ptosis as its primary complication of interest and reports no observed cases among 4,000 patients evaluated at follow-up. Eyebrow ptosis was separately reported in 16 patients, corresponding to 0.4%.
The authors also mention the ‘quizzical’ or ‘cocked’ eyebrow—an aesthetic asymmetry caused by uneven frontalis activity—as a relatively frequent minor issue in clinical practice. Because the study was retrospective, this outcome was not systematically recorded and was not included in the formal adverse-event analysis.
How Do These Results Compare With Prior Literature?
The discussion contrasts the study’s approximately 6% adverse-event incidence with previously published literature. It cites a systematic review and meta-analysis by Jia and colleagues reporting a statistically significant increase in adverse events with botulinum toxin type A compared with placebo, and another review reporting an overall complication rate of 16%, with many events described as mild and transient.
This comparison is useful context, but it is not a randomized head-to-head comparison between strict aftercare and simplified aftercare. Differences in populations, products, doses, injection techniques, definitions and follow-up can all influence reported complication rates.
Suggested Patient-Facing Aftercare Box
After your appointment: Your treatment plan and aftercare may vary according to the botulinum toxin product, treatment area, dose, anatomy, medical history and bruising risk. The study reviewed in this article suggests that many prolonged behavioral restrictions may be less evidence-based than traditionally believed. Follow the specific instructions provided by your treating clinician, particularly if your treatment was complex or you have individual medical considerations.
When Should a Patient Contact the Clinic?
The source article does not provide a formal emergency algorithm. For website publishing, a conservative patient-safety message can be included as an editorial addition rather than as a study finding:
- Unexpected or progressive eyelid droop.
- Marked or worsening facial asymmetry.
- Concerning weakness outside the expected treated area.
- Visual symptoms.
- Severe, progressive or otherwise unusual symptoms after treatment.
FAQs
How long should I stay upright after Botox?
Traditional advice often recommends staying upright for several hours. In the 5,014-patient retrospective study reviewed here, patients were observed for only 10 minutes and then resumed normal activities. The study questions a universal four-hour rule, but it did not randomize upright versus lying-down groups.
Can I lie down after Botox?
The study challenges prolonged positioning restrictions, but it did not separately test lying down versus remaining upright. It therefore does not prove that positioning never matters.
Can I sleep after Botox?
The source study did not specifically study sleep. It supports reconsidering prolonged restrictions but cannot establish a precise evidence-based ‘safe sleeping time.’
Can I exercise after Botox?
Patients in the study resumed normal activities after the initial 10-minute observation period, but strenuous exercise was not independently tested. The evidence therefore questions routine restriction without proving equivalence for every intensity of exercise.
Can I go to the gym after Botox?
The study was not designed as a gym or high-intensity exercise trial. A universal answer cannot be derived from it, although the simplified protocol did not require prolonged activity restriction.
Can I bend over after Botox?
Bending over was not independently randomized or measured in the study. The findings weaken the rationale for rigid prolonged positioning rules but do not prove that bending has zero effect in every situation.
Can I massage my face after Botox?
The paper discusses local, dose-dependent diffusion but did not randomize massage versus no massage. It would therefore be inaccurate to say massage is proven harmless immediately after treatment.
Can I use ice after Botox?
Cooling is commonly used for bruising and swelling, but the paper discusses preliminary evidence suggesting temperature may influence toxin translocation. More research is needed.
Can I go in the sun or sauna after Botox?
Avoiding sun and heat is a traditional recommendation listed in the paper, but the study did not isolate sauna or heat exposure as a separate randomized variable.
What is the most common side effect in this study?
Mild bruising was the most common recorded adverse effect, reported in 3% of the evaluated follow-up cohort.
How common was eyebrow ptosis?
Eyebrow ptosis was reported in 16 patients, corresponding to 0.4% in the study’s adverse-event table.
How common was upper-eyelid ptosis?
No upper-eyelid ptosis was observed among the 4,000 patients who attended clinical follow-up. This does not mean the complication is impossible; it means no cases were observed in that evaluated cohort.
Were patients satisfied without strict aftercare?
Yes. Among 2,010 questionnaire respondents, 90% were satisfied or very satisfied.
Does Botox migrate around the face?
The paper argues that local, dose-dependent diffusion is a more accurate concept than uncontrolled migration. Dose, placement and injector technique remain important.
What matters most for safe upper-face Botox?
The paper emphasizes local toxin behavior, appropriate dose and injection technique. Patient selection, anatomy and clinician expertise remain central even when prolonged aftercare restrictions are questioned.
Is this study enough to change all Botox aftercare rules?
No. It is a large retrospective study, but it has no randomized control group and uses descriptive statistics. Prospective randomized research is still needed.