
What Is the Midface ?
The source chapter defines the midface as the area between the lower eyelid and the oral commissure. Although this sounds simple, aesthetically it is one of the most complex regions of the face because it connects the eye, nose, cheek, nasolabial fold and lower face.
A youthful cheek is not merely “big.” It is naturally projected, adequately supported over the zygomatic arch and maxilla, and blends smoothly into the lower eyelid and surrounding facial regions. Abrupt shadows, flattened projection or visible compartment boundaries can make the face appear tired or aged.
How the Midface Ages
Midface aging is a layered process. The chapter describes changes in the facial skeleton, deep and superficial fat, retaining ligaments, mimetic muscles and skin. Genetics and baseline anatomy influence how early or late these changes become visible.
With aging, the orbital floor and pyriform aperture enlarge inferiorly and laterally, and the maxillary and malar framework provides less support. At the same time, fat compartments can lose volume or shift, producing flattening, hollows and deeper transition lines.
Deep vs Superficial Fat Compartments : Why the Difference Matters
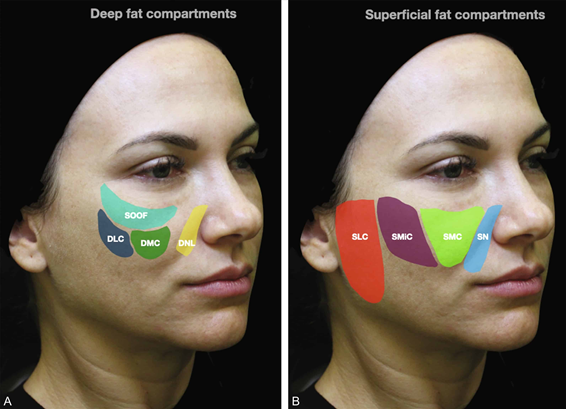
The midface is compartmentalized rather than filled by one continuous layer of fat. The source identifies deep compartments such as the deep nasolabial compartment, deep medial cheek, deep lateral cheek and medial/lateral SOOF, along with superficial nasolabial and malar compartments.
This distinction is clinically important because deep volume replacement can restore support and projection, while superficial treatment is more useful for fine contour refinement and smoothing transitions. Treating the wrong layer can produce heaviness or an unnatural surface contour.
Retaining Ligaments, Septa and Dynamic Support
Important midface retaining structures include the orbital retaining ligament, malar septum or zygomatic-cutaneous ligament, and the zygomatic or MacGregor patch. The chapter also describes a transverse facial septum related to the zygomaticus major muscle that helps support deep cheek fat compartments.
During smiling, contraction of the zygomaticus major may tension this septum and shift midface fat cranially, which illustrates why facial movement should be considered during assessment rather than evaluating a completely static face only.
Vascular Anatomy and the Angular Artery
The facial artery and its branches are highly relevant to midface filler safety. The source describes the facial artery crossing the lower mandibular border, traveling upward and becoming the angular artery as it courses toward the nose and periorbital region.
Because of its location and vascular connections, the chapter identifies the angular artery as the vessel most likely to be compromised after filler injections to the midcheek, nasolabial fold and periorbital region. This is one reason midface filler should be viewed as a medical procedure rather than a routine cosmetic service.
The Ogee Curve : A Better Goal Than Simply “Bigger Cheeks”
The chapter describes the ideal cheek as an S-shaped Ogee curve: a concave arc from the lower eyelid, a convex malar or cheekbone prominence, and a gentle transition into the submalar hollow. Restoring this contour can create rejuvenation without making the face look overfilled.
What is the Ogee curve ?The Ogee curve is the natural S-shaped contour of a youthful midface, formed by a gentle concavity below the eye, convex cheek projection and a soft transition into the submalar region.
Male vs Female Midface Contouring
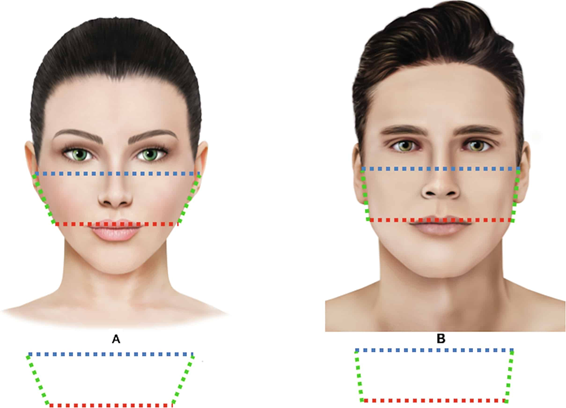
The source chapter describes important average differences in midface proportions. In women, the bizygomatic width is commonly greater than the bigonial width, creating a stronger midface relative to the lower face. In men, the two widths are closer, contributing to a squarer facial outline.
The female cheek apex is described as higher, more lateral and more ovoid, while the male cheek often has a broader malar base and a more modest apex positioned slightly more inferomedially. These are planning references rather than rules; treatment should be individualized to the patient’s own facial anatomy and desired aesthetic.
Facial Shape Matters : Angular, Heart, Oval and Round Faces
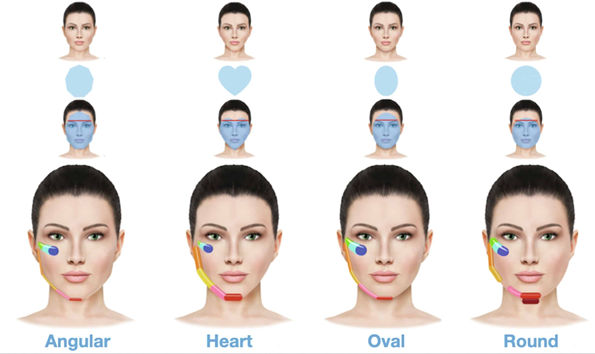
One of the strongest planning concepts in the chapter is that treatment priority changes with facial shape. The Anatomy of Beauty approach describes angular, heart, oval and round facial formats and uses filler strategically to preserve strengths, improve proportions and avoid making every face look the same.
For example, the chapter notes that the angular face may benefit from more emphasis on the midface, whereas the heart-shaped face may have relatively greater lower-face treatment priorities. This supports a central principle of modern aesthetic medicine: the correct treatment is not determined by the hollow alone but by the whole facial framework.
Structure First, Refinement Second
The source divides treatment into two conceptual stages. The structural stage focuses on restoring support, volume and proportions. The refinement stage addresses remaining grooves and transitions so that treated areas blend naturally with one another.
This approach helps avoid a common aesthetic mistake: directly filling every line or hollow before restoring the deeper support that created the problem in the first place.
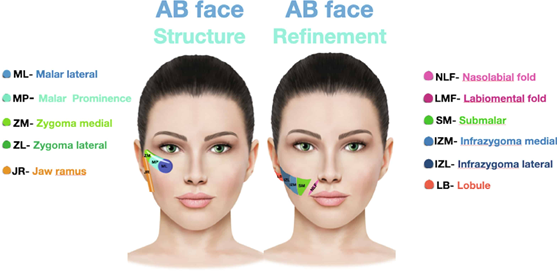
Main Midface Treatment Areas
1. Malar or Anterior Cheek Region
The malar region is a major structural target for midface rejuvenation. The chapter emphasizes restoration of malar fat and SOOF-related volume to recreate anterior cheek projection and improve the lower-eyelid-to-cheek transition.
It also cites surface-volume research suggesting that SOOF compartments have a high surface projection response, meaning that relatively small changes in deeper support may translate into visible surface contour improvement.
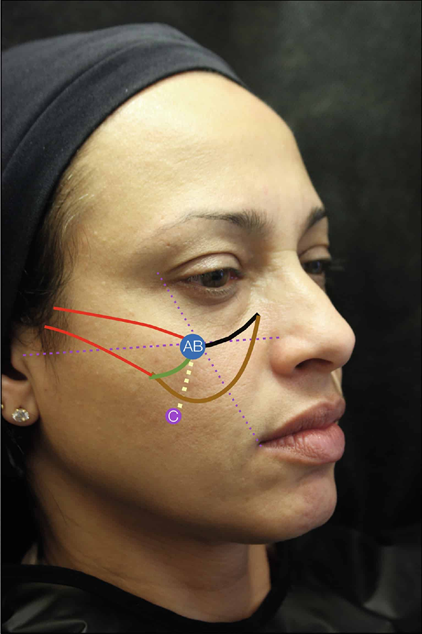
2. Zygomatic / Lateral Cheek Region
The zygomatic region contributes to lateral cheek support and the contour of the zygomatic arch. The chapter explains that age-related retraction and volume loss in this area can be treated to improve the lateral midface and lower-eyelid appearance.
The key aesthetic objective is not simply to create a sharply projected cheekbone, but to rebuild a smooth, age-appropriate framework that integrates with the anterior cheek.
3. What Can Midface Filler Change ?
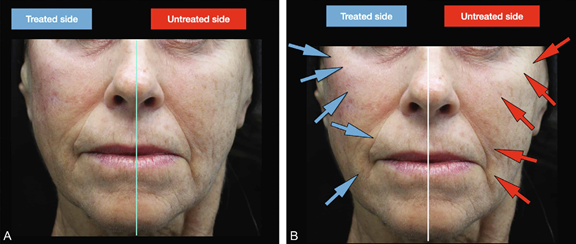
According to the source chapter, midface augmentation can influence more than cheek volume alone. By restoring structure and refining transitions, treatment may improve the eyelid-cheek junction, malar projection, selected nasojugal or palpebromalar grooves, nasolabial fold appearance and the overall frame of the cheek.
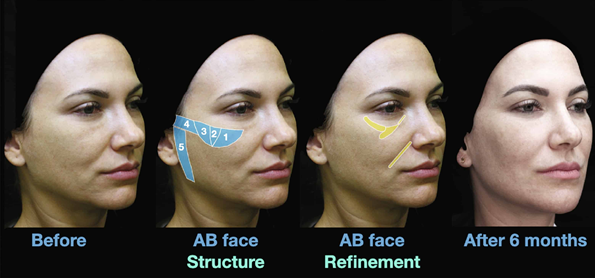
4. Submalar Region: Restoring a Hollow Without Overfilling
The submalar hollow is part of the natural Ogee curve. The chapter therefore does not advocate erasing every shadow. Instead, the goal is to replace excessive volume loss while preserving enough natural concavity to keep the cheek apex defined.
This is particularly important in very lean or athletic patients, where deeper volume depletion may be prominent. Overfilling the submalar area can transform an oval contour into a rounder, heavier-looking face.
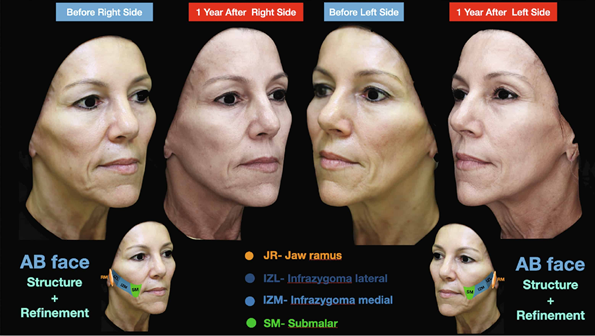
5. Preauricular / Lateral Cheek Region and the Line of Ligaments
The chapter uses the concept of the line of ligaments to explain why filler placed in different parts of the face can create different visual effects. Lateral treatment tends to create more lifting or support, whereas medial treatment tends to create more volumization and projection.
Treating the preauricular or lateral cheek region can help complete the “frame” of the cheek, particularly when lateral soft-tissue depletion interrupts a smooth transition from the midface to the side of the face.
HA Filler vs Calcium Hydroxyapatite for the Midface
The source chapter places biodegradable HA fillers at the center of nonsurgical midface rejuvenation and also discusses calcium hydroxyapatite as an effective option, particularly when diluted and used for selected superficial or subdermal contour indications.
| Product family | Role in the source chapter | Practical treatment concept |
|---|---|---|
| Hyaluronic acid (HA) | Primary biodegradable filler for structural restoration and contour refinement | Product characteristics can be selected for deeper support versus softer superficial transitions; HA is also reversible with hyaluronidase. |
| Calcium hydroxyapatite (CaHA) | Can be used alone or with HA; diluted CaHA is discussed for selected submalar/lateral superficial treatment | More relevant to support and biostimulatory remodeling than to creating a soft, highly mobile superficial fill. |
| Biostimulatory strategy | The chapter supports biostimulators as part of nonsurgical midface rejuvenation | Best used when the treatment goal includes tissue quality or broader support rather than simply replacing one focal hollow. |
How to Avoid an Overfilled Midface
A natural midface should still have highlights and shadows. The chapter specifically warns that excessive filling of the submalar region can convert an attractive oval contour into a rounder, heavier-looking face. This is closely related to the broader concept of facial overfilled syndrome discussed in the chapter’s references.
- Restore deeper structural support before chasing every superficial line.
- Preserve the natural submalar shadow instead of erasing all concavity.
- Match cheek width and apex position to the patient’s facial shape.
- Avoid treating a female face with an excessively broad, low cheek if the goal is a softer or more oblique contour.
- Avoid forcing a high, lateralized cheek on a male face when it disrupts natural male proportions.
- Use the smallest amount of product that produces a meaningful change and reassess facial balance.
Who May Be a Good Candidate for Midface Filler ?
The source chapter does not provide a rigid candidate checklist, but its treatment framework is most applicable to patients with age-related or anatomical loss of cheek projection, flattening of the malar region, visible transition lines between the eyelid and cheek, disproportionate facial shape or selected submalar and lateral cheek volume loss.
A consultation should also determine whether the patient’s concern is truly volume loss. Some shadows may reflect skin quality, lower-eyelid anatomy, ligament position, bone structure or lower-face descent, and may not be best treated by simply adding filler.
Safety : Why Midface Filler Requires Detailed Anatomy
The source repeatedly emphasizes that knowledge of the midface skeleton, fat compartments, retaining ligaments, muscles and vascular risk zones is crucial to achieve good results and avoid complications.
The angular artery is specifically highlighted as the vessel most likely to be compromised during injections involving the midcheek, nasolabial fold and periorbital region. The artery can follow variable paths, and the rich vascular connections of the central face make careful anatomical planning essential.
Patient-facing safety pointMidface filler should be performed by an appropriately trained medical professional who understands facial vascular anatomy, recognizes complications early and has a clear management plan. No injection technique eliminates risk completely.
How Long Do Midface Results Last ?
This chapter illustrates outcomes at 6 months and 1 year in selected cases, but it does not establish one universal duration for every filler or patient. Longevity depends on the product, treatment layer, amount, metabolism, anatomy and treatment objective.
The safest patient-facing wording is therefore to discuss expected duration for the exact product being used rather than promise one fixed number of months for all cheek fillers.
Can Cheek Filler Improve the Nasolabial Fold or Under-Eye Transition ?
Yes, in selected patients. The chapter shows that restoring midface structure can improve adjacent transitions, including the eyelid-cheek junction and the appearance of the nasolabial fold. This does not mean every tear trough or nasolabial fold should be treated indirectly through the cheek; the cause of the fold or hollow must first be identified.
